
A GLP-1 physician survey Saudi Arabia teams can use has to start from the published papers, then ask what those papers left out. A GLP-1 medicine copies a gut hormone. Doctors use some of them for diabetes and for weight loss. The papers below are surveys of clinicians. They are not a count of patients on treatment, and they are not a national sales figure. This page sits on the healthcare market research hub and the healthcare market research page for Saudi Arabia, next to obesity and GLP-1 research in Saudi Arabia and who does obesity market research in Saudi Arabia.
What should the survey answer?
A brand team usually needs four answers. Who starts a medicine. Which molecule they choose. What blocks the prescription. Whether that pattern differs by specialty, city and sector. A published knowledge quiz can be a baseline. It does not replace a study built around one decision.
What have published surveys found?
Four clinician surveys are the public baseline. A fifth study, from Qassim University, mixes physicians with nurses and pharmacists. The table uses each paper’s own methods.
| Study | Fielded | Sample | Who was asked |
|---|---|---|---|
| AlOtaibi et al., 2025 | May–August 2024 | 92 clinicians | Family physicians, endocrinologists and one bariatric surgeon |
| Alrasheed et al., 2026 | December 2024–November 2025 | 399 physicians | Family medicine, internal medicine, endocrinology, cardiology and nephrology |
| Turjoman et al., 2025 | Published March 2025 | 51 physicians | Family medicine and internal medicine at National Guard, Madinah |
| ACTION-IO Saudi Arabia (Alfadda et al., 2021) | June–September 2018 | 200 HCPs and 1,000 people with obesity | Primary care and specialists; bariatric surgeons were ineligible |

A 2024 survey of 92 clinicians
AlOtaibi and colleagues ran an online survey from May to August 2024. They invited family physicians, endocrinologists and bariatric surgeons. Ninety-two clinicians finished it. The authors could not calculate a response rate. Cronbach’s alpha was 0.75. The ethics approval number was 2024-86.
The sample was 64.1% male. Mean age was 37.4 years (standard deviation 10.2). Family medicine was 77.2%. Endocrinology was 21.7%. Bariatric surgery was 1.1%. Nearly half, 44.6%, had practised for fewer than five years. The Central region was 59.8% of respondents. The governmental sector was 67.4%. Only 15.3% had obesity-focused training.
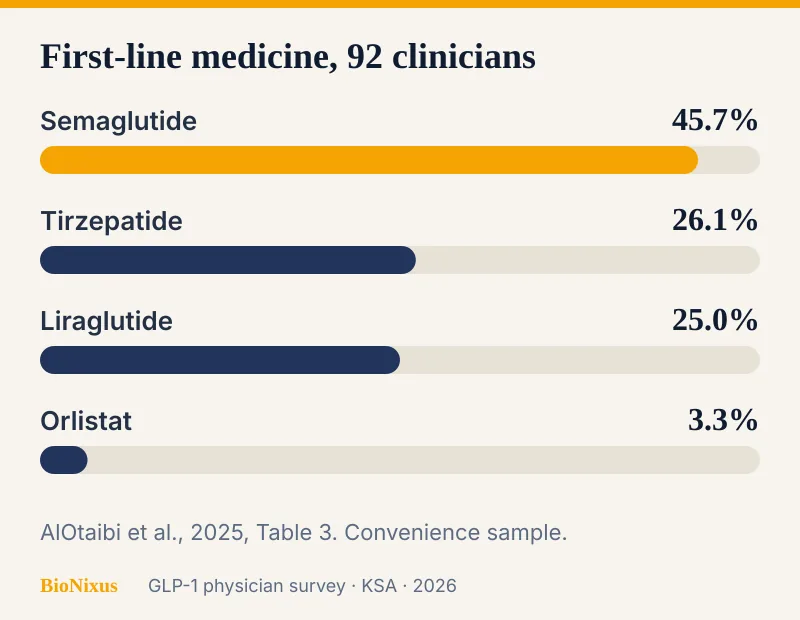
On a select-all question, 97.8% named a GLP-1 receptor agonist and 44.6% named a dual GIP/GLP-1 agonist. On a separate question that asked for one first-line agent, 45.7% chose semaglutide, 26.1% tirzepatide, 25.0% liraglutide and 3.3% orlistat. The paper’s prose calls 97.8% first-line. Table 3 keeps the two questions apart. Use the table. The 97.8% figure is not a national share.
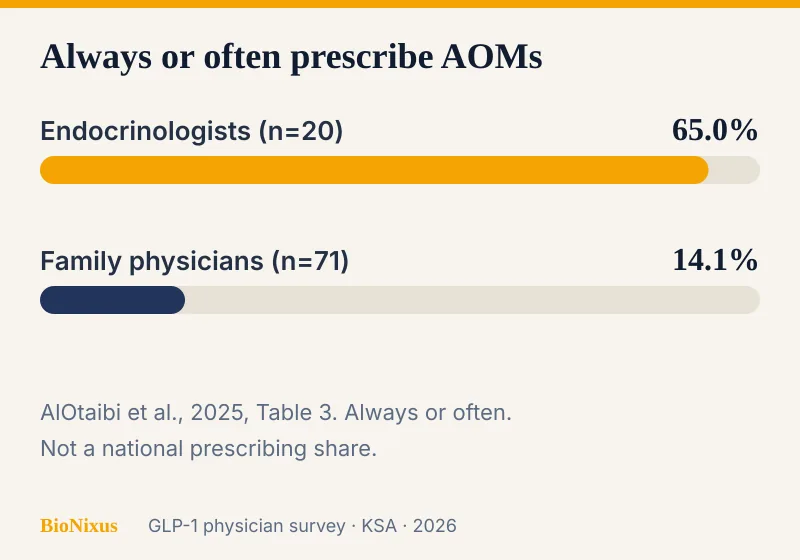
Overall, 25.0% prescribed anti-obesity medicines in the paper’s two highest frequency answers, 42.4% sometimes, and 32.6% in the two lowest answers. Endocrinologists were in the two highest answers at 65.0%. Family physicians were at 14.1%. Adding the middle answer, 90.0% of endocrinologists and 60.6% of family physicians prescribed at some frequency. The odds ratio for endocrinology and more frequent prescribing was 9.97 (95% confidence interval 3.36 to 29.60). For family medicine it was 0.11 (0.32 to 0.40). Prior obesity training had an odds ratio of 2.45 (1.07 to 5.64).
When choosing between a GLP-1 and a dual agonist, 83.7% cited availability, 47.8% effectiveness and 45.7% dosing frequency. Cost influenced the choice for 75.0% of endocrinologists and 36.6% of family physicians. Insurance did so for 45.0% and 18.3%. Prescription limits were named by 33.8% of family physicians and 10.0% of endocrinologists. The authors note that some hospitals limit these medicines to endocrinologists.
Family physicians were more likely to name the Saudi guideline (46.5%). Endocrinologists were more likely to name AACE/ACE (75.0%). For indications, 79.3% used a body mass index over 30. And 52.2% used a body mass index of 27 to 29.9 with a weight-related condition.
A 2024–25 survey of 399 physicians
Alrasheed and colleagues surveyed 399 physicians who regularly manage type 2 diabetes, from December 2024 to November 2025. They could not calculate a response rate. Among 351 physicians with a sub-specialty, family medicine was 177 (50.4%), internal medicine 114 (32.5%), endocrinology 37 (10.5%), cardiology 15 (4.3%) and nephrology 8 (2.3%). Specialists were 59.6% of the sample, residents 24.8%, general practitioners 12.0% and consultants 3.5%. Most practised in Riyadh (71.7%).
Adequate knowledge meant at least five of eight items correct. That bar was met by 91.0% for SGLT-2 inhibitors and 78.4% for GLP-1 receptor agonists. Only 23.6% met the authors’ bar for a positive attitude. Appropriate practice was met by 75.4%. The GLP-1 knowledge scale had a KR-20 of 0.37. Treat 78.4% as a score on a weak scale, not as a national competency rate. Attitude Cronbach’s alpha was 0.70. Practice was 0.80.
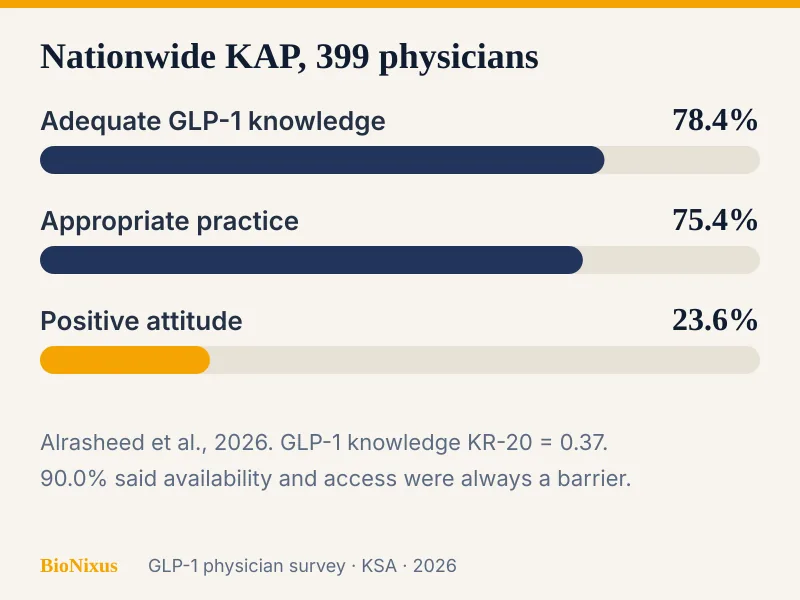
Availability and patient access were a barrier on the paper’s strongest response for 90.0% of respondents (359 of 399). When benefits and risks were similar, 35.6% preferred an SGLT-2 inhibitor over a GLP-1 on that same strongest response. Attitude and practice were the most strongly correlated pair (Spearman ρ = 0.67). After adjustment, ages 56 to 65 had higher odds of inappropriate practice than ages 25 to 35 (adjusted odds ratio 8.68, 95% confidence interval 2.34 to 37.2). Specialists had lower odds than general practitioners (0.23, 0.09 to 0.57). GLP-1 knowledge was not independently tied to practice in that model. The authors also cite a Saudi review in which 19% of eligible patients with type 2 diabetes received an SGLT-2 inhibitor or a GLP-1 receptor agonist. That 19% is the review they cite. It is not this survey’s own count of patients.
Fifty-one physicians in Madinah
Turjoman and colleagues surveyed 51 physicians at Prince Mohammed bin Abdulaziz Hospital and its primary-care clinics. The ethics number was KAIMRC western-region IRB 2453/23. The paper was received on 26 November 2024 and published on 23 March 2025. Internal medicine was 58.8%. Family medicine was 41.2%. Most respondents were under 35 (92.2%) and had two years of experience or less (62.7%). Only 13.7% were board-certified. Authority to prescribe a GLP-1 was yes for 25.5%, no for 72.5% and unknown for 2.0%.
The median knowledge score was 10.0 of 13 (interquartile range 8.0 to 11.0). Knowledge items were scored correctly by 77.2%. In one cut, good knowledge was 49.0%, fair 31.4% and poor 19.6%. Good attitude was 19.6%, fair 17.6% and poor 62.7%. Good practice was 23.5%, fair 17.6% and poor 58.8%. On a different cut, 51.6% showed a positive attitude and 55.2% showed good practice. Family medicine had a higher share of good knowledge than internal medicine (66.7% versus 36.7%). Board-certified physicians had good practice at 71.4%, against 13.0% of residents. The authors say not every physician at the site finished the form.
ACTION-IO in 2018
The Saudi arm of ACTION-IO (Alfadda et al., 2021; ClinicalTrials.gov NCT03584191) surveyed 1,000 people with obesity and 200 healthcare professionals between June and September 2018. Of the people with obesity, 46% had received an obesity diagnosis, 44% had a follow-up appointment, and 5% had kept their weight loss for more than a year. Bariatric surgeons were not eligible. This was fielded before current GLP-1 use for weight loss. It is a conversation baseline. It is not a prescribing share. The healthcare-professional form took 28 minutes.
A mixed sample in Qassim
Aldhobaib and colleagues approached 154 health professionals at Qassim University in 2020–21 (ethics 20.02.08). One hundred and twelve agreed (72.7%) and 107 were analysed after five incomplete forms were dropped. About half were physicians, 33.6% were nurses and 16.8% were pharmacists. Overall correct response was 73.5% for knowledge, 78.5% for attitude and 80.3% for practice. This is a campus sample of several professions. It is not a national physician survey.
Where do these surveys stop?
- AlOtaibi and Alrasheed could not calculate a response rate. Turjoman says the form was not completed by every physician on site. Do not treat any percentage as a national share.
- AlOtaibi has 20 endocrinologists and one bariatric surgeon. Alrasheed has 37 endocrinologists, 15 cardiologists and eight nephrologists. Those cells are small.
- AlOtaibi’s Central share is 59.8%. Alrasheed’s Riyadh share is 71.7%. Other regions are thinly measured.
- Alrasheed’s GLP-1 knowledge KR-20 is 0.37. AlOtaibi’s 97.8% is a select-all class question.
- In the Eastern Province, 40.4% of GLP-1 users paid themselves and 59.6% had insurance or government support (Alhussain et al., 2026). That patient survey is not a physician survey.
Alhussain’s survey covered 1,264 adults with overweight or obesity in December 2024. Lifetime GLP-1 use was 18.2%. Current use was 14.2%. Among users, 70.4% started on a doctor’s recommendation and 36.5% on their own decision. The paper also notes a Ministry of Health campaign, launched in August 2025, on prescription rules for weight-loss medicines. Tobaiqy and colleagues surveyed 365 adults who had used an anti-obesity medicine at three hospitals in Jeddah between June 2025 and February 2026. Alhomoud and colleagues surveyed 211 community pharmacists in Qassim. High medicine cost was named as a barrier by 67.3%. A physician survey does not replace those studies.
How should you design the next one?
Set the smallest cell first. Then build the total. Name endocrinology, family medicine, internal medicine and bariatric surgery as separate cells. Record whether the respondent may prescribe before you ask what they prescribe. Keep class, molecule and line of therapy as separate questions. Split governmental and private practice. Do not let Riyadh fill the sample. Field in Arabic and English. ACTION-IO’s professional form took 28 minutes. A shorter form is easier to finish.

For how interviews are run, see physician surveys in Saudi Arabia.
What does Saudi data law require?
The Personal Data Protection Law applies to personal data in the Kingdom. It classes health data as sensitive data (SDAIA guide; law text). Ask how consent, storage and transfer will work, and who owns the file after delivery. ACTION-IO named Novo Nordisk as sponsor. A custom study can hide the product name. It still has to name the fieldwork firm to the respondent.
How to brief BioNixus
BioNixus is a primary market research firm for pharmaceutical, medical device and healthcare companies. It was founded in 2012. It has served 118 clients in 48 countries. It has run 127 studies so far in 2026. It works with a network of 82,000+ physicians globally and about 3,200 physicians in the Middle East. Custom studies are usually priced at $10k–$60k. Leadership offices are in Sheridan, Wyoming, London EC1V 2NX, and Sheikh Zayed, Giza. There are a field office for UAE in Dubai, a partner office for KSA in Al Khobar, and a field office for Kuwait in Salmiya. São Paulo is a field office for LATAM. Work in Latin America is covered today from the US office with local consultants.
The line “Guaranteed in writing” covers the agreed scope, timing and deliverables. It does not cover what the interviews will find. BioNixus has 40 client reviews.
To brief a study, use the contact form or email admin@bionixus.com.
References
- AlOtaibi HF, et al. Saudi Healthcare Providers’ Perspectives and Clinical Practice of Anti-Obesity Medications: A National Survey. Saudi J Med Med Sci. 2025;13(3):222–230. doi:10.4103/sjmms.sjmms_672_24. Source (accessed 12 October 2026).
- Alrasheed MA, Alhadhrami BM, Alqarni AA, Alghamdi NM, Alfurayh OA, Almohammed OA. Knowledge, attitudes, and practices of Saudi physicians toward the use of SGLT-2 inhibitors and GLP-1 receptor agonists in patients with type 2 diabetes mellitus: a nationwide cross-sectional study. Front Endocrinol. 2026;17:1929125. doi:10.3389/fendo.2026.1929125. Source (accessed 12 October 2026).
- Turjoman MA, Mahrous A, Ozbuk AA, Alhujaili RM, Bagasi HT, Alsiary KA. Knowledge, Attitude and Practice about Glucagon-like Peptide-1 Receptor Agonist Among the Physicians of Prince Mohammed bin Abdulaziz Hospital & Primary Health Care, National Guard, Saudi Arabia. J Pharm Res. 2025;24(1):36–44. doi:10.18579/jopcr/v24.i1.71. Source (accessed 12 October 2026).
- Alfadda AA, et al. Perceptions, attitudes, and barriers toward obesity management in Saudi Arabia: Data from the ACTION-IO study. Saudi J Gastroenterol. 2021;27(3):166–172. doi:10.4103/sjg.sjg_500_20. ClinicalTrials.gov NCT03584191. Source (accessed 12 October 2026).
- Aldhobaib AY, Rabbani SI, Mobark MA. Knowledge, Attitude and Practice about a Newer Class of Antidiabetic Drug (Glucagon-like peptide-1 receptor agonist) Among the Health Care Professionals of Qassim University, Saudi Arabia. J Pharm Res. 2021;20(4):58–66. doi:10.18579/jopcr/v20i4.MS21083. Source (accessed 12 October 2026).
- Alhussain K, et al. Prevalence and Factors Associated with GLP-1 Receptor Agonist Use for Weight Management Among Overweight and Obese Adults in the Eastern Province of Saudi Arabia. Healthcare (Basel). 2026;14(3):345. doi:10.3390/healthcare14030345. Source (accessed 12 October 2026).
- Tobaiqy MA, et al. Patient Experiences and Safety Concerns Regarding GLP-1 Receptor Agonists for Obesity: A Cross-Sectional Survey in Jeddah, Saudi Arabia. Saudi Med J. 2026;47(9):1516–1523. doi:10.15537/1658-3175.8842. Source (accessed 12 October 2026).
- Alhomoud IS, et al. Knowledge, Counseling Practice, Perceived Barriers, and Clinical Decision-Making of Community Pharmacists in Saudi Arabia Regarding Glucagon-Like Peptide-1 Receptor Agonists and Sodium-Glucose Cotransporter 2 Inhibitors. Diabetes Metab Syndr Obes. 2025;18:3093–3107. doi:10.2147/DMSO.S552287. Source (accessed 12 October 2026).
- Saudi Data & Artificial Intelligence Authority (SDAIA). Guide to the Saudi Personal Data Protection Law. Source (accessed 12 October 2026).
- SDAIA. Personal Data Protection Law (English translation), including the classification of health data as sensitive data. Source (accessed 12 October 2026).




